
How consistent is embryo grading? What the research actually shows
Ten senior embryologists, 100 IVF cases, one question: which embryo to transfer? They fully agreed in half. Here is what the evidence says about grading variability.
Garbha.ai Team
AI & Embryology Research
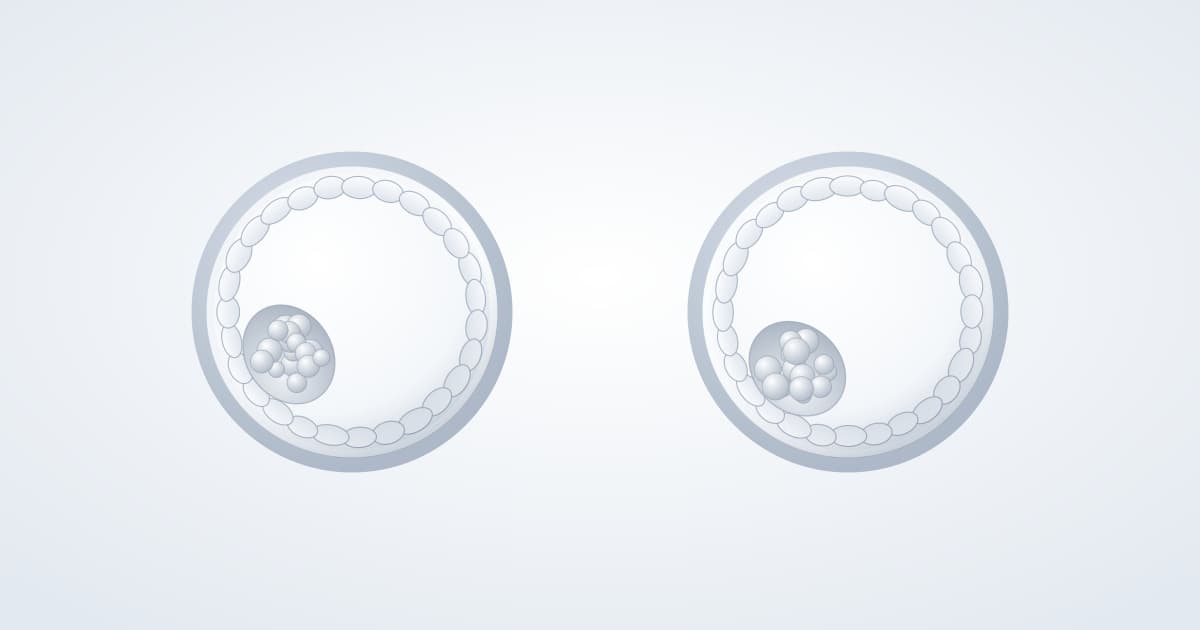
Embryo grading is less consistent than most people outside the laboratory assume. In a multicentre study of ten senior embryologists across five IVF clinics, all ten chose the same Day-5 embryo for transfer in exactly half of the 100 cases presented to them.1 Agreement on the individual components of the grade was weaker still. Grading is a skilled judgement, and skilled judgements vary.
This is not a criticism of embryologists. It is a well-documented property of any system that asks a human to convert a continuous visual impression into a discrete category, and the profession has been measuring and publishing it openly for years. What follows is what that literature actually says.
Key takeaways
- Ten senior embryologists shown the same 100 IVF cases agreed unanimously on which Day-5 embryo to transfer in 50 of them.1
- Agreement on the components of the grade was only fair: inner cell mass κ = 0.349, trophectoderm κ = 0.397.1
- Two ESHRE-certified embryologists assigned the same morphological grade to the same blastocyst in 55 of 99 cases (κ = 0.448).2
- The same embryologist, re-grading the same blastocysts two months later, agreed with their own earlier assessment at only κ = 0.495.2
- Scoring the same embryos by morphokinetics instead of static morphology raised inter-observer agreement to κ = 0.795, and concordance to 83 of 99 cases.2
What is embryo grading, and what does a grade like 4AA mean?
Embryo grading is the visual assessment an embryologist performs to decide which embryo to transfer. For a Day-5 blastocyst, the widely used Gardner system produces a grade with three parts: a number for how far the blastocyst has expanded, then two letters — the first for the inner cell mass, which becomes the fetus, and the second for the trophectoderm, which becomes the placenta.
So a grade of 4AA describes an expanded blastocyst with a well-formed inner cell mass and a well-formed trophectoderm. A grade of 3BC describes a less expanded blastocyst with a moderate inner cell mass and a sparser trophectoderm. Our guide to embryo development from Day 1 to the Day-5 blastocyst covers this progression in more detail.
The system is detailed and clinically useful. It is also, unavoidably, an act of interpretation. There is no measuring instrument that reads out "A" or "B" — a trained professional looks down a microscope and decides.
How often do two embryologists give the same embryo the same grade?
Less often than the precision of the grading vocabulary implies. In a prospective multicentre study, ten embryologists — selected as the top performers on their organisation's quality assurance programme — independently reviewed 100 IVF cases comprising 428 embryos across five clinics.1 Asked which single Day-5 embryo they would transfer, all ten agreed in 50 of the 100 cases. At least six of the ten agreed in 93 cases.
The overall agreement statistic for that transfer decision was good (κ = 0.734). But when the same study examined agreement on the underlying morphological grades rather than the final choice, the picture changed sharply: inner cell mass κ = 0.349 and trophectoderm κ = 0.397, both of which fall in the range conventionally described as only fair.1
That gap is the most interesting finding in the paper. Experienced embryologists converge reasonably well on the practical question — which one do we transfer? — while disagreeing considerably about the descriptive grades they would write in the notes. The decision is more robust than the vocabulary used to justify it.
A second study found a similar pattern with a different design. Two ESHRE-certified embryologists, with five and ten years of experience, independently graded 99 blastocysts with known implantation outcomes. They assigned the identical Gardner grade in 55 of 99 cases (κ = 0.448 — moderate).2
Does the same embryologist agree with themselves?
Not entirely, and this is the finding that tends to surprise people most. In that same study, each embryologist re-graded the same 99 blastocysts a second time, two months later, blinded to their original assessment. Their agreement with their own earlier grades was κ = 0.495.2
The same professional, the same images, moderate agreement. This is a well-recognised phenomenon in every field of image-based medical assessment, from radiology to histopathology, and it is precisely why measurement variability is treated as a property of the method rather than a failing of the person.
It also reframes the problem usefully. If the variability were purely a matter of differing skill between individuals, the remedy would be training. Intra-observer variability of this size tells us the remedy has to be something else.
Why is embryo grading so subjective?
Three reasons, and they compound.
The categories are discrete but the biology is continuous. An inner cell mass does not arrive as an A or a B. It exists somewhere on a smooth spectrum of cell number and cohesion, and the grader has to place a boundary. Embryos near that boundary will be graded differently by different people — and by the same person on different days.
Grading is a snapshot of a process. Conventional assessment captures the embryo at one or two fixed timepoints. Two embryos that look identical at the moment of assessment may have arrived there along quite different developmental paths, and that path carries information the static image does not.
Conditions vary between laboratories. Culture media, incubator conditions, stimulation protocols and patient populations all differ between clinics, and grading conventions drift accordingly. A grade is not a fully portable unit of measurement across labs.
Does the disagreement actually matter for outcomes?
Partly, and it is worth being precise about where it does and does not.
The reassuring finding is that agreement was highest on the decision that matters most — which embryo to transfer — and lowest on the descriptive components.1 In a cycle with one clearly superior embryo, most embryologists will pick the same one.
The disagreement bites in the harder cases: cohorts where several embryos are of similar quality, and cohorts of uniformly borderline embryos where the question is not only which to transfer but which to freeze and which to discard. Those are exactly the cases where a consistent, reproducible second read has the most to offer — and, not coincidentally, the cases embryologists find most demanding.
It also matters for anything built on top of the grade. Cross-clinic outcome comparisons, quality benchmarking, training assessments and research datasets all treat the grade as though it were a stable measurement. The evidence above suggests treating it with more caution than that.
What reduces the variability?
The clearest signal in this literature concerns what is being assessed rather than who is assessing it.
When the same two embryologists scored the same 99 blastocysts using morphokinetic parameters — timings of specific developmental events extracted from time-lapse imaging — instead of static morphology, inter-observer agreement rose from κ = 0.448 to κ = 0.795, and concordance rose from 55 to 83 of 99 cases. Intra-observer agreement rose from κ = 0.495 to a mean of κ = 0.735.2
That is a substantial improvement, and the mechanism is straightforward: a timing is a measurement, whereas a morphological category is a judgement. Annotating when an event occurred is a more reproducible task than deciding how good something looks.
This is the honest case for automated, quantitative assessment. Not that software sees things humans cannot, but that measuring is more reproducible than judging.
Does AI solve this?
It addresses the consistency problem directly. It has not yet been shown to improve pregnancy or live birth rates, and anyone claiming otherwise is ahead of the evidence.
The largest randomised trial in this area is worth stating plainly. In a multicentre, double-blind, non-inferiority randomised controlled trial across 14 IVF clinics in Australia and Europe, 1,066 patients were randomised to embryo selection by a deep-learning algorithm or by standard morphology. The AI arm did not meet the criteria for non-inferiority: clinical pregnancy was 46.5% versus 48.2%, and live birth 39.8% versus 43.5%.3 A separate randomised trial of time-lapse imaging itself found no live-birth benefit over conventional culture and assessment.4
So the current evidence does not support the claim that AI embryo selection produces more babies.
What the same randomised trial did find is a roughly ten-fold reduction in embryo evaluation time.3 Read alongside the reproducibility findings above, that points to where AI embryo grading genuinely earns its place today: consistency, throughput, and a stable reference point that does not vary between two embryologists or between the same embryologist on a Monday and a Friday.
There is one further caveat the field is still working through, and it deserves to be said by vendors rather than only by critics. A 2025 study trained 50 identically designed neural networks that differed only in random initialisation. They achieved near-identical accuracy scores — and still ranked the same patient's embryos in materially different orders, with concordance of only κ ≈ 0.35 and critical error rates reaching 21% and higher at one centre.5 An accuracy figure alone says very little about whether a model is stable. Ranking consistency, external validation across sites, and explainability are the properties that actually matter, and they are the ones a laboratory should ask about.
The 2025 update to the ESHRE/ALPHA Istanbul consensus on embryo morphological assessment issues no formal recommendation on artificial intelligence. Its discussion describes AI as holding great promise to augment the embryologist's assessment, but says it should not yet be considered a replacement for conventional assessment.6 The field is genuinely early.
What this means for your laboratory
- Measure your own concordance. Have two embryologists independently grade the same set of blastocysts, and calculate agreement. Most laboratories have never done this, and the number is usually informative.
- Treat grading variability as a quality metric, not an embarrassment. It is measurable, it is improvable, and it belongs in your quality management system.
- Look hardest at the borderline cohorts. That is where variability changes decisions.
- When evaluating any AI tool, ask about stability, not just accuracy. Specifically: what is the ranking concordance across model runs, and what happened to performance when it was validated at a clinic whose data it had never seen? A vendor who cannot answer those two questions has not finished the work.
What this means if you are a patient
If your clinic gave you an embryo grade, it is a genuine and useful piece of information — but it is an expert visual assessment, not a laboratory measurement like a blood test. A different embryologist might have graded it slightly differently, and that is normal and openly documented in the professional literature.
Two things follow. A lower-graded embryo is not a failed embryo; grades shift the odds, they do not determine the outcome. And it is entirely reasonable to ask your clinic how they grade embryos, whether more than one embryologist reviews the decision, and whether they use time-lapse or software-assisted assessment. Good clinics welcome these questions.
Where Garbha.ai fits
Garbha.ai is a CDSCO-licensed AI decision-support platform for the IVF laboratory. Its embryo assessment module produces a consistent, quantitative assessment of each embryo alongside the embryologist's own, with Grad-CAM heatmaps showing which regions of the image drove the score, so the output can be interrogated rather than merely accepted. It runs on-device inside the lab, and is designed to address the reproducibility problem described in this article. The embryologist remains the decision-maker, and the software does not diagnose, treat, or guarantee an outcome.
Frequently asked questions
Is embryo grading subjective?
Yes, to a measurable degree. Embryo grading is an expert visual assessment rather than an instrument reading. In a multicentre study, ten senior embryologists agreed unanimously on which Day-5 embryo to transfer in 50 of 100 cases, and agreement on the individual grade components — inner cell mass and trophectoderm — was only fair.
Do two embryologists give the same embryo the same grade?
Not always. In one study, two ESHRE-certified embryologists assigned the identical Gardner grade to the same blastocyst in 55 of 99 cases, a moderate level of agreement (κ = 0.448). Agreement is generally higher on the practical question of which embryo to transfer than on the descriptive grade itself.
Is a 4AA embryo guaranteed to work?
No. A 4AA grade describes an expanded blastocyst with a well-formed inner cell mass and trophectoderm, and such embryos have better average outcomes. But grading shifts probabilities rather than determining them, and many pregnancies come from embryos graded lower than 4AA.
Does AI grade embryos more accurately than embryologists?
AI grades embryos more consistently, which is a different claim. The largest randomised controlled trial of AI embryo selection did not demonstrate non-inferiority to standard morphology on pregnancy or live birth rates. The demonstrated benefits so far are reproducibility and a substantial reduction in evaluation time.
Does time-lapse imaging make grading more reliable?
It improves assessment reproducibility. When the same embryologists scored the same blastocysts using morphokinetic timings instead of static morphology, inter-observer agreement rose from κ = 0.448 to κ = 0.795. However, a large randomised trial found that time-lapse imaging did not increase live birth rates compared with conventional culture.
Should I ask my clinic how they grade embryos?
Yes. It is a reasonable question and a well-run laboratory will answer it readily. Useful things to ask: whether more than one embryologist reviews the selection, whether the lab uses time-lapse or software-assisted assessment, and how they handle cases where several embryos are of similar quality.
References
- Storr A, Venetis CA, Cooke S, Kilani S, Ledger W. Inter-observer and intra-observer agreement between embryologists during selection of a single Day 5 embryo for transfer: a multicenter study. Human Reproduction. 2017;32(2):307–314. doi:10.1093/humrep/dew330
- Adolfsson E, Andershed AN. Morphology vs morphokinetics: a retrospective comparison of inter-observer and intra-observer agreement between embryologists on blastocysts with known implantation outcome. JBRA Assisted Reproduction. 2018;22(3):228–237. PMID: 29912521
- Illingworth PJ, Venetis C, Gardner DK, Nelson SM, Berntsen J, Larman MG, et al. Deep learning versus manual morphology-based embryo selection in IVF: a randomized, double-blind noninferiority trial. Nature Medicine. 2024;30(11):3114–3120. doi:10.1038/s41591-024-03166-5
- Bhide P, Chan DYL, Lanz D, et al. Clinical effectiveness and safety of time-lapse imaging systems for embryo incubation and selection in IVF (TILT): a multicentre, three-parallel-group, double-blind, randomised controlled trial. The Lancet. 2024;404:256–265. doi:10.1016/S0140-6736(24)00816-X
- Thirumalaraju P, Kanakasabapathy MK, Kandula H, et al. Stability and reliability of artificial intelligence models in embryo selection for in vitro fertilization. Fertility and Sterility. 2026;125:277–286. doi:10.1016/j.fertnstert.2025.08.021
- Working Group on the update of the ESHRE/ALPHA Istanbul Consensus. The Istanbul consensus update: a revised ESHRE/ALPHA consensus on oocyte and embryo static and dynamic morphological assessment. Human Reproduction. 2025;40(6):989–1035. doi:10.1093/humrep/deaf021
Medical disclaimer: This article is for educational purposes and is not medical advice. Decisions about fertility treatment should be made with a qualified reproductive medicine specialist who knows your clinical history.
Related articles
How AI helps select sperm for ICSI — and what the evidence actually says
AI can measure how each sperm moves during ICSI. Here is what randomised trials and Cochrane reviews say about sperm selection methods so far.

AI embryo grading explained: from Day 1 to the Day-5 blastocyst
How AI reads an embryo's development day by day — morphokinetics, fragmentation and the blastocyst — to bring objectivity and consistency to embryo selection in IVF.
Revolutionizing IVF: How Garbha.ai is transforming embryo selection for higher success rates
Infertility challenges millions worldwide. Garbha.ai's deep-learning approach to embryo grading brings precision and objectivity to IVF — and renewed hope to families.
Book a demo
See Garbha.ai in your clinic
Book a personalised demo of our AI-powered IVF solutions.